Monday, January 09, 2006

An Unwanted Journey: Day 0046 - First Treatment


I may have to be more careful about what I listen to on the radio while driving to treatment at the Grand River Regional Cancer Centre these days (GRRCC). But it was strangely compelling material that Shelagh Rogers and Syd Birrell were discussing – Ya Can’t Let Cancer Ruin Your Day, a book of emails from Syd about his young son’s battle with a malicious form of cancer called neuroblastoma. I tried to tell my wife about the interview when I met her at the GRRCC, but found that the words caught in my throat and I couldn’t finish – the first of three times during the day when tears caught me unexpectedly.

I will purchase the book, but will have to be judicious about when I read. Today, for instance, despite my eagerness to get treatment underway, I found myself almost suffocated by cancer treatment and the reality of my situation. There were so many appointments, so much information, so little personal control over anything that was being done to my body…everything was just too much.

We started with a blood draw in the chemo suite followed quickly by a teaching session with one of the pharmacists in something euphemistically called a “quiet room”. This was all about 5-FU (fluorouracil), side effects, the kind of Baxter “baby bottle” pump I would be wearing (this was unexpected; I was told earlier that I would have a pump in the shape of a money belt with a keypad protected by a password, something far smaller than the “baby bottle” with a hip pouch which I now have), and the rate of flow by which the 5-FU will enter my blood stream (1.5 ml / hr).

We had time for lunch in the hospital cafeteria and a quick visit to the computer/resource centre (which doesn’t allow for access to My CARE Source, unfortunately, nor for outside access through Remote Desktop, something I need to get into the corporate network where I work most of my days) before on to the 5-FU infusion. The oncology nurse hooked me up very quickly and then presented me with this “baby bottle” which I will have connected to me for the next 6 weeks. She showed me how to care for the bottle and offered suggestions for how to wear it. She also showed me my blood test results from earlier in the day; evidently my liver function and kidney function are both good. My ANC (absolute neutrophil count, calculated by multiplying the total white blood count times the neutrophil count) is well within the appropriate range for chemotherapy.

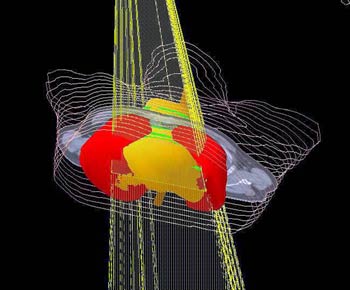
And then it was on to radiation therapy. Again, I felt my emotions right at the surface – so little control, such a sense of both unreality and super-realism to everything happening around me, and incredulity that all this was being done “to” me. The radiation procedure and machine are impressive and the treatment painless. There were no expected “blocks” on the treatment bed since those are now built in to the machinery itself and controlled through computer software settings. These blocks are about 6 inches thick and made of an alloy that includes the expected lead protection. I get three “blasts” of radiation each day, one to the back of the pelvis and one to either side.

But it wasn’t over. We then moved on to the pharmacy to pick up an anti-emetic to combat nausea if I encounter that side-effect, a “spill” kit for the chemo, some special cream to treat the skin at the location of the radiation fields, and a special pouch to hold my chemo bottle. We picked up more “veterinary” gloves for bathing, collected our literature, hoisted my notebook computer and left for home. In the parking lot, though, we met an acquaintance surprised to see us at the hospital. It was the third such encounter of the day, one of which was another patient in the cancer centre itself, someone who was the crossing guard for our children in kindergarten.

We went home, unpacked all the pharmaceutical products, tried out various ways of securing the chemo bottle, took my temperature with the digital thermometer provided by the GRRCC pharmacy to cancer patients…and then I crashed for a while, sleeping for about forty minutes.

This was a tough day, but my wife was very supportive, helping me bathe in the evening, shopping with me to get appropriate shirts that would work well with the apparatus I have to carry everywhere with me, preparing my supper, and helping me remember everything that happened today. I don’t know how I could handle all this without her.

Tomorrow (Tuesday), it’s merely a physical with my family physician, a consultation with the radiation oncologist, another trip to the pharmacy for my medical supplies, and…oh yeah…more radiation therapy.

Sunday, January 08, 2006

An Unwanted Journey: Day 0045 - Day Before Treatment


This is the final day before treatment. Diagnosis, although not complete until the post-surgical pathology report, is as complete as it can be. I’ve had all the important tests and images, the insertion of the PICC line, my medical team is in place with a well-conceived plan ready to implement, home nursing is already attending to my needs, friends and family and colleagues are aware of what I will be going through and many have been incredibly supportive, I’ve started a nutritional plan and a physical training plan with clear objectives…everything is ready to go.

No doubt there will be a few more surprises, maybe some side effects to cope with, possibly some surgical complications, and undoubtedly some tough days when my spirits are low. But I feel ready, in fact eager, to begin treatment. Apart from the occasional moments when I still find myself thinking, “What? Me? Cancer? You got to be kidding!”, I’m approaching this with real optimism and a solid belief that I can beat this thing.

Here we go!

Saturday, January 07, 2006

An Unwanted Journey: Day 0044 - PICC and pickin'


Medical Stuff
Today (Saturday), the Community Care Access Centre of Waterloo Region (CCAC) nurse came to our house to change the dressing and flush the line for the PICC catheter (peripherally inserted central venous catheter). Since this was the first visit from the CCAC (delivered through CarePartners), we had to go through another health questionnaire. We also discussed the details of how often nurses would be visiting me at home to change the dressing. Evidently the chemotherapy nurses will flush the line weekly when I visit the Grand River Regional Cancer Centre (GRRCC) on Mondays, but the CCAC nursing team will visit me at home once a week to change the dressing, probably on Friday mornings.

My wife and I watched the procedure carefully, just in case we have to perform the procedure ourselves. It is a sterile procedure which means that the nurse and patient both have to wear masks (I only have to do so if I want to face the nurse and watch the procedure, which I do). Removing the tape, swabbing the insertion point in gradually larger circular movements first on-time with hydrogen-peroxide and a second-time with povidone-iodine, allowing time for drying, and then reapplying the see-through tape are fairly straightforward. There is no pain involved except for the removal of bandages which usually means pulling out hairs on the arm.

The PICC line I have in place uses a needle-less injection cap (CLC2000®). This prevents blood from backing up into the catheter as well as enabling the delivery of fluids and medications into the blood system. The line itself has a single lumen (central channel in the line). The nurse uses a syringe from a medical kit which I pick up from the home care department of the Grand River Hospital’s main pharmacy. Medical supply kits can be picked up from the pharmacy on Tuesday or Friday afternoons. Each syringe has either a saline solution to flush the line or a heparin solution to prevent blood clotting in the line. Injecting the solutions requires carefully eliminating any air in the syringe and then very gradually injecting the solution. Quick or forceful movements could be dangerous, especially if there is a blockage already in the line which could then be forced out into the blood system.

Home Stuff
I’ve been meaning to play the guitar for quite a while now, but realized this morning when I actually took my Tacoma Chief (C2C) out of its case that I hadn’t touched it since being diagnosed with cancer in late November. Prior to that, I had been practicing my fingerstyle Christmas songs and carols. Today, however, my fingers could only take a few minutes of play. This may be a good thing; I am forced to think more about music and music theory if I want to get back at the guitar. Today, for instance, I found myself running through chord progressions and trying to write out chord frames and progressions on sheet music. I’ve never done this seriously before, so maybe my illness will be the occasion to try on something new with the guitar.

A good friend, whose father passed away from colorectal cancer and who has been writing to me regularly since my diagnosis, has been forwarding photographs of his guitar and amplifier collection. These are primarily investment opportunities for him, but I’m sure the pure aesthetic delight of seeing these one-of-a-kind beauties is just as important to him. He certainly has me salivating over some items in his collection.

In any case, I’m hoping now that I’ve actually picked up my guitar again that some of the shock of my diagnosis has diminished and that I can enjoy music wholeheartedly again. Instead of the PICC line, maybe I can concentrate more on picking the guitar.

Friday, January 06, 2006

An Unwanted Journey: Day 0043 - PICC Insertion


It was a long day at the Grand River Regional Cancer Centre, probably the first of many such days.

It all makes sense in retrospect – an early lab appointment for a baseline blood draw, followed by about a 90-minute delay until I saw the PICC line (peripherally inserted central venous catheter) nurse. That time was required for the systemic oncologist to see the blood measures and approve moving ahead with the PICC insertion.

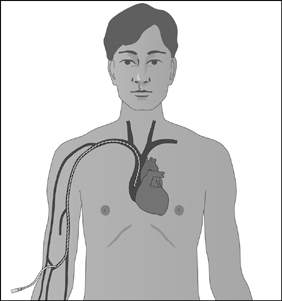
The insertion of the PICC catheter was more involved than I anticipated as well. It required a sterile environment that was novel for me. The PICC nurse had to find a vein that would work; unfortunately mine was on my right arm even though I am right-handed. Thank goodness most of my work is at the computer keyboard. Then, she had to don special gloves, mask, and gown, measure the distance from the vein she had chosen up my arm to a position just above the heart. After cutting the length of catheter required, she had to sterilize the site for the insertion, freeze it with a local anaesthesia, insert the catheter, flush the line with a saline solution (which I tasted almost immediately), followed by another flush with a solution of heparin (which I smelt almost immediately).

After she was assured that I was alright, an orderly took me in a wheelchair for X-rays of my chest to ensure that the PICC catheter was in exactly the right location just above the heart. If it was too long, she would have to cut some off the length; if too short, she would have had to re-measure and re-insert another line. As it turned out, this PICC nurse knew her craft perfectly and had measured precisely what I needed as verified by the X-rays.

I then had to visit the hospital pharmacy to pick up a starter kit for taking care of possible spills as well as changing the dressing and flushing the line. Saturday morning, I will be visited by a Community Care Access Centre of Waterloo Region nurse who will demonstrate the changing of dressings and flushing the line.

One of the things the PICC nurse and I discussed was what activities I can and cannot do during the next 6 weeks while the line is in place. Basically, I can’t shovel snow, I can’t sweep floors, I can’t vacuum the carpet – I can’t do weight training exercises that involve the arms in any serious way. No curls, no lunges, no woodchoppers, no push-ups, no bench presses. My trainer and I will have to adjust the core training regimen somewhat. The squats should be alright as will the sit-ups on the stability ball, the Roman chair knee raises, and bosu squats. I’ll schedule an appointment with a physiotherapist on the system oncologist’s team to ensure I don’t do anything potentially damaging to the PICC line.

Infection is the chief worry. Draining from the exit point that is clear, yellow, or green requires seeing one of the CCAC nurses as soon as possible. Any fever requires an immediate visit to either the GRRCC or the hospital emergency department. Finally, redness around the insertion site could lead to phlebitis, but can be controlled with warm, moist compresses applied every 2 or 3 hours.

Waiting is boring, there’s no doubt about it. But today I was able to read through both the chemotherapy and radiation therapy booklets provided for patients by the Canadian Cancer Society as well as the additional booklet about Caring For Your PICC Catheter from Cook (Canada) Inc.

This weekend is the end of the pre-treatment phase. Monday I start both chemotherapy and radiation therapy.

Thursday, January 05, 2006

An Unwanted Journey: Day 0042 - My PICC


Tomorrow is the final preparation before treatment begins. There will be a blood draw in the lab as well as the insertion of the PICC (peripherally inserted central catheter).

The blood work will provide a baseline for the efficacy of the chemoradiotherapy, monitoring haemoglobin, platelets, red blood cells, alkaline phosphatase, carcinoembryonic antigen, creatine, and many other measures. I will be able to monitor these weekly scheduled measurements through My CARE Source online.

The PICC line is plastic tube which will be inserted into a hole created in a vein with a needle near the bend in the elbow. The tube is then pushed through until the tip is close to a large vein just above the heart. It is likely that I will then have an X-ray to ensure that the PICC is in exactly the right location.

There are a variety of reasons to have a PICC for the cancer patient. One reason is to avoid constantly using needles to draw blood. Another is to make it easier to provide chemotherapy and antibiotics directly into the blood stream, especially where the drugs can be quickly diluted by fast flowing blood in one of the major veins near the heart.

The PICC will probably be in my arm for a few months, being flushed and the dressing changed weekly. There are some potential medical problems such as infection or clots, but the advantages seem very clear to me. Exercise, dressing and undressing, showering, etc. may be uncomfortable. If I’m lucky, my personal trainer may figure she needs to be more lenient with me in our training sessions.

Wednesday, January 04, 2006

An Unwanted Journey: Day 0041 - Tattoos & Training


Normally I refuse to make New Year’s Resolutions. But here’s one that works – this year I resolve to be the first person in my immediate nuclear family to get a tattoo. OK, there’s one resolution that’s already implemented.

Today was my radiation planning and simulation at the Grand River Regional Cancer Centre. It began with an orientation session with an oncology nurse who explained what they were going to do, why the procedures were done this way, and what to expect as I entered the room where the radiation oncology CT scan machine is located. She also gave me one of those wonderful contrast solutions to drink similar to those I had to consume for my previous diagnostic CT scan and MRI.

So, for yet another of what will undoubtedly be many more exercises of undressing and putting on those flimsy hospital gowns, I prepared for the procedure. When I entered the room with the CT scan, another technician took my photograph with a digital camera and then asked me to lie face down on the CT scan bed. I had to maintain that position for about 20 minutes or so, not the most comfortable of positions, especially since I couldn’t see anything and had my buttocks exposed to the world. I guess dignity flies out the window during rectal cancer treatment. This isn’t a complaint about the nurses and technicians. They do everything in their power to make the patient feel comfortable, but this isn’t exactly what I had in mind when I’ve fantasized about two women asking me to get undressed.

They had to position me a couple of times on the table to eliminate any twisting of the torso, followed by a pilot scan. After that, they marked the middle of the back of my pelvis and the sides with a marking pen, ran the CT scans, asked me to wait in the face-down position for another 10 minutes while they viewed the photographs, and then proceeded with the tattoo.

The tattoo is really just some small blue dots used to triangulate the location of the tumour and the pelvis where the radiation treatment will be focused. I was a “jumper”. The tattoo on the back was easy, but the one on my left side for some reason caused a nervous twitch. Luckily my “jumping” didn’t require doing the tattoo over again.

Generally, it takes a couple of weeks for the planning of the radiation treatment; this involves the preparation of the blocks and templates used to shield the rest of the body from radiation and to help position the body for the daily treatments. In my case, since the team is moving ahead quickly and because the chemotherapy is to be executed at exactly the same time, the two weeks was reduced to just a few days. Later in the day, I noticed that my radiation treatment schedule was already in place on the GRRCC’s My CARE Source website for patients.

I will be getting about 54.9 Gray (Gy) in 28 fractions for the radiation treatment schedule (The gray is a unit used to measure a quantity called absorbed dose. This relates to the amount of energy actually absorbed in some material, and is used for any type of radiation and any material. One gray is equal to one joule of energy deposited in one kg of a material. The unit gray can be used for any type of radiation, but it does not't describe the biological effects of the different radiations. Absorbed dose is often expressed in terms of hundredths of a gray, or centi-grays. One gray is equivalent to 100 rads.)

A little later in the morning, I had another session with my fitness trainer at Popeye’s Gym. She has me performing a core training regimen that involves lots of stability exercises, abdominal exercises, stretching, squats, push ups, lunges and other assorted exercises. She indicated that it is a fairly advanced routine. I’m progressing reasonably well already, increasing repetitions and the weight for various sets. But by the end of our session, I felt like I’d like to go back to bed. Oh well, just another 12 weeks of this torture before surgery. Maybe when all the treatment and training is finished, I’ll see about connecting those dots and getting myself an interesting tattoo.

Tuesday, January 03, 2006

An Unwanted Journey: Day 0040 - Hostility


In retrospect, there were many ways in which I could have reduced hostility and the resultant harm that inevitably comes from experiences of hostility, either directed outwards towards others or directed from others towards me. I’m not sure such experiences in my life are a contributing cause for my colorectal cancer, but I am sure that living with as little hostility as possible has to be beneficial to one’s health.

So, I’ve chosen to postpone investigating guided imagery until I’ve had further consultations with staff at the Grand River Regional Cancer Centre. Instead, being a verbal guy anyway, I’ve decided to focus my immediate attention on the gentle art of verbal self-defence (see Suzette Haden Elgin’s books, one being Staying Well With the Gentle Art of Verbal Self-Defense).

I’ve already written about arguing with oneself and the means by which we can deflate hostility which we might wittingly or unwittingly direct inwards towards ourselves.

What I haven’t written about in any detail is how the mere fact of writing a journal of both facts and feelings about my experience with cancer is itself therapeutic. All of these things are connected, according to Elgin. Our struggle with language, our commitment to use metaphors consciously, our willingness to debate both external and internal voices – all of these boosts the immune system. And, of course, we know that anything which boosts the immune system is bound to be beneficial to the cancer patient.

Coping with cancer invariably involves feelings of hostility and anger, denial and distraction, blame and fear. Writing about such feelings prevents them from worming their way into our physical structures and doing additional damage to what the cancer itself has already done. So the very act of writing journal entries is a kind of gentle verbal self-defence.

For those who don’t have a comfort level with writing a diary, Elgin suggests some “training wheels” like the following hostility template:

Date:__________

When ___________________________________________ today,
I felt ________________________, because _____________________.

For example, I might use this template to write “When I was told that surgery may cause irreparable harm to urinary and sexual function today, I felt an incredible sense of loss and despair, because nowhere in my research had anyone written that I should expect incontinence or impotence.”

Something happens in doing these kinds of exercises, something soothing and energizing at the same time. Writing about feelings isn’t just about venting. It’s about linking aspects of reality with the emotional life. In the case of the example above, the when clause refers to a verifiable fact. It happened and anybody that was there can verify the fact. The because clause is also a verifiable fact of reality, although here I am speaking about something which I alone have discovered in my research. As long as I am honest, then we have a second fact-based clause. The I felt is the only part of this tripartite template which references the internal life. But most observers should be able to observe the coherence of my internal feelings with my outer behaviour. In other words, it isn’t entirely subjective.

There is a useful discipline here. By creating a linkage between objective reality and subjective reality, I have disabled the inchoate expression of unhelpful and destructive emotions. There is nothing wrong with expressing one’s emotions, but the discipline is about grounding those emotions in observable, objective reality. We move from hostility towards healing.

Sunday, January 01, 2006

An Unwanted Journey: Day 0038 - Visualization


“By visualizing the immune system actively attacking the cancerous growth, the immune system is mobilized, strengthened, and its natural antagonism toward cancerous growth is reawakened. In this way, the person participates in his or her own treatment, a kind of psychic biofeedback which increases the will to live.” – from Psychotherapeutic Treatment of Cancer and the Consciousness Restructuring Process, 2000.

I find myself somewhat trapped. If, as seems to be the case with my meandering thoughts, my mind can influence the future of the body, then the corollary appears to be that in the past my mind was already influential in the development of cancer. Not a comforting thought!

But maybe that is the price that must be paid to embrace the possibility of contributing to one’s own healing. After all, conventional treatment hardly ever talks about visualization and meditation, and when it does, it does so in the context of adjusting to one’s predicament. This is most obvious in the hospice setting where the focus for visualization and meditation exercise is on dying with dignity. The attitude seems to be that being at peace emotionally can’t hurt the situation. But implying that a patient may somehow have been a participant in the onset of cancer one might do more harm than could possibly be warranted by quickly issuing the corollary that this means the patient can contribute to his/her own healing. Far easier to simply recommend practices to ease pain and be at peace than to go out on a limb and suggest self-healing has true potency.

Bernie Siegel is one conventional practitioner, a surgeon, whose books demonstrate his willingness to risk the implication of self-blame. He does so because of his conviction that self-healing occurs regularly with what he calls his ECaPs (Exceptional Cancer Patients). Love, Medicine & Miracles and Peace, Love & Healing are two of his books in my library that I intend to re-read right away. Another book which I’ll digest shortly afterwards will be Suzette Haden Elgin’s Staying Well With The Gentle Art of Verbal Self-Defense; she recommends Siegel’s books enthusiastically. Whereas Siegel uses drawings and images as primary tools for self-healing, Elgin uses metaphors and verbal constructs for self-protection and self-healing.

Siegel makes a comment in the introduction to Peace, Love & Healing which helps alleviate the self-blame implicit in recognizing that our thoughts, emotions, and attitudes may have predisposed us to cancer in the first place. In fact, his view is that whatever the truth of that proposition, it is something simply not useful to pursue - something akin to Martin Seligman’s recommendations about arguing with oneself by considering the usefulness of a proposition.

“However, those of you who feel guilt because you believe you have caused your own illnesses, or who feel like failures if you cannot cure them, are giving your healing system a destructive message. You must let go of feelings of guilt and failure so that, unencumbered by these negative messages, you can utilize to the fullest your innate healing capacities.” – p.4

I guess this implies that we need to let go of the past simply because we can’t do anything about it anyway; but the future is something we can influence with the power of imagery, metaphor, and optimism.

Saturday, December 31, 2005

An Unwanted Journey: Day 0037 - TME


As 2005 closes with a diagnosis of rectal cancer, 2006 approaches with the prospect of chemoradiotherapy, surgery and more chemotherapy. All treatments are important, but surgery is clearly the most invasive and possibly curative of the three. I turn my attention to the intention of my surgical oncologist to use a technique called TME or total mesorectal excision. My academic training as an historian sometimes affects how I conduct research into important issues in my life. Here is what I’ve found about surgical techniques for rectal cancer. (Much of what follows comes directly from the article The Role of Total Mesorectal Excision in the Management of Rectal Cancer, published in 2002.)

Early Treatment
Ernest Miles first described abdominoperineal resection in 1908 (abdominoperineal resection is a surgical procedure in which both the rectum and the anus are removed from the patient, thereby requiring a colostomy, an opening in the abdominal wall by which to connect the remaining colon and replace the anus; the patient is thereby left with a device for the remainder of his life to handle defecation). By the 1920s, this surgical method had reduced rates of recurrence of rectal cancer from almost 100% to about 30%. The practice became the gold standard for surgical treatment of rectal cancer for many years even though there were still significant recurrence rates and urinary, sexual and gastrointestinal side-effects.

Mid-Century Treatment
By the 1950s, anterior resection (a portion of the rectum is removed and the remaining ends are joined) replaced abdominoperineal resection as the surgical standard treatment for rectal cancer. One of the distinct advantages for patients in this approach was the possibility of avoiding a colostomy. Unfortunately, there continued to be significant concern about recurrence rates.

Current Treatment
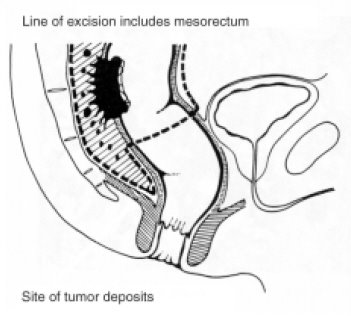
Then, in 1982, total mesorectal excision was first described by RJ Heald and his colleagues. The TME procedure is based on complete removal of the mesorectum, the tumour and as much of the rectal tissue as necessary. The mesorectum is the rectal mesentery, a membranous fold of lymphatic vessels, lymph nodes and fatty tissue which is itself contained within a thin membrane called the mesorectal fascia containing the rectum, the mesorectum and the lymph nodes. A major goal of TME surgery is to remove the mesorectum intact. Why? Because the blood supply and lymphatic drainage for the rectum are contained in the mesorectum. If the mesorectum is removed, the chances of cancer cells spilling during surgery and remaining in the abdominal region are greatly reduced. TME has been shown to reduce rates of recurrence to as low as 4% after 5 years from the time of curative surgery.

Now, TME is considered the gold standard for surgical treatment of middle and lower-third rectal cancer in most of Europe, with many advocates in the United States and Canada. But the technique is difficult and requires great skill on the part of the surgeon conducting the 3- to 5-hour procedure. In fact, of all major surgically treated cancers, outcomes for rectal cancer treated with TME are the most dependent on the technical skills and experience of the surgical oncologist.

Monitoring Skill Level
Heald recommended an audit method for surgeons utilizing TME techniques. It is called the Quirke-based method for histopathological study of the excised specimen. Dr Phil Quirke promoted the circumferential margin involvement (CMI) of the TME specimen as a significant indicator of local recurrence of cancer. In other words, the pathologist has to examine the circumference of the specimen very carefully to determine how far from the outer edge of the specimen cancer cells are located. Generally, if there is a margin of 1 mm for the entire circumference, then it is designated as “clear”. In addition, the pathologist has to assess 12 or more lymph nodes to ensure there are no metastases of the cancer.

Standardization of both terminology and technique is progressing. As of 1999, surgical oncologists agreed to dispense with other names for the surgical technique and agreed to settle on TME. In Canada, it appears that at least some provinces are moving towards standardizing on Quirke-method histopathology techniques thereby allowing better evaluation of surgical expertise.

Problems
There continue to be problems with TME for the patient. Leakage rates from the anastomatic resection and the inability to defer defecation in lower rectal resections, especially in lower rectal resections, continue to be problematic. If nerve-sparing techniques are utilized in TME, there is mounting evidence that urinary and sexual function can be spared, but patients should be prepared psychologically for potential problems.

Future Directions
Laparoscopic surgical techniques for total mesorectal excisions may become more common. A study from 2001 assessed open surgery and laparoscopic-assisted surgery (far smaller incisions for the patient); in that study, it was estimated that up to 50% of patients would benefit without compromising survival and recurrence rates. Another presentation by Michelle K. Smith at the 8th World Congress of Endoscopic Surgery in which 112 consecutive patients in 3 centres in France from 1991 to 2001 were treated with laparoscopic TME suggests that laparoscopic TME may even be superior to open surgery insofar as there is improved visualization, it is easier to determine correct anatomical planes, and there is improved ability to standardize and teach the technique to other surgical oncologists.

Friday, December 30, 2005

An Unwanted Journey: Day 0036 - Down The Rabbit Hole


“How far down the rabbit hole are you prepared to go?”

“It makes you think, doesn’t it? If thoughts can do that to water, imagine what our thoughts can do to us.”

Two separate scenes from a movie that is on my top ten list – What The Bleep Do We Know? (a sequel will be released in February 2006 entitled What The Bleep – Down The Rabbit Hole).

The first quote is an obvious reference to Alice in Wonderland. The second is made by Armin Shimerman, the actor best known for his portrayal of the Ferengi bartender Quark in Deep Space Nine. He is talking to the character portrayed by Marlee Matlin about an exhibit he and she are currently viewing of an experiment done by a Japanese scientist (Dr Masaru Emoto) in which the effects of thoughts and blessings on ordinary water are documented with photographs. What is so extraordinary about the exhibit and the photographs is that they clearly show how thoughts and feelings affect the physical reality of water crystals. Words are spoken or “sent” by focused intention to the frozen water which then responds by changing its “expression”. Negative thoughts or polluted water sources have a distinctly “ugly” expression compared to the beautiful expressions arising from positive thoughts or clean water sources.

The implications for cancer patients from both the movie and Dr Masaru Emoto’s experiments relate directly to my reflections over the past couple days about “arguing with oneself” and “prayer”. They relate as well to the increasingly persuasive and sophisticated science of positive psychology promoted by Dr Martin Seligman. The bottom line is fairly simple to state: there is mounting evidence that prayer, love, good intentionality, optimism, and happiness affect physical reality in ways modern, flatland science would never have imagined only a few short years ago.

Does this mean those of us afflicted with cancer can heal ourselves? Well, that’s another question entirely and I simply don’t have an answer yet. But whatever the complexity of the subject, whatever the limitations of this emerging science, whatever the hurdles we face in empowering individuals to apply some of the lessons of quantum physics to self healing…there is reason to hope, there is reason to be optimistic, there is reason to be kind and to love one another.

Thursday, December 29, 2005

An Unwanted Journey: Day 0035 - Prayer


Yesterday, I was blessed with two people praying for me out loud, one after a visit to our home by relatives, the other on the telephone with a friend whom I haven’t seen for a very long time. In both cases, they asked if I would mind if they prayed for me. In both cases I accepted, and in both cases I felt blessed.

So how does the perennial skeptic deal with this rationally?

Yesterday I wrote about arguing with oneself, about the process we all engage in daily of hearing voices asking questions, offering answers, making speculations, and so on. I suggested that there was no more credibility to the voices inside our head than to those we hear in dialogue with other people. I advised disputing the conclusions and assumptions of the voices within by using evidence, alternatives, implications, and usefulness of ideas. The point of arguing with oneself is to generate optimistic thoughts and emotions, something which we all know instinctively heal the spirit if not the body.

But then it occurred to me – is there any difference between arguing with oneself and prayer?

When friends and relatives pray out loud for you in your presence, there is a different tone and attitude expressed than when you are both engaged in dialogue. Extemporaneous prayers of petition express generosity and good will toward the one who is ill; that much is clearly obvious. But they also express the highest aspirations and dignity of the human spirit (OK, not always, but most of the time) for the wellbeing of another person; they do so in the guise of a personal petition to God.

But if both religion and the meaning of cancer are best understood as human creations, then prayer can be understood as a special kind of human dialogue whose purpose is to heal the sick. Not cure the illness, but heal the sickness.

We might not agree with one another about the nature of the universe, about the existence of a supernatural god, or even about the meaning of cancer. But when someone prays for you, especially out loud in your presence, the invitation is to a dialogue of healing. I can’t see anything wrong with this, as long as the individual being prayed for can separate his own worldview easily from that of the person praying for him. If the prayer is a genuine expression of a desire for healing, and if it doesn’t bludgeon the individual being prayed for with too many ill-conceived ideas, then it can be truly useful.

There are still some sticking points that I need to work on here. If prayer by another person who believes in a supernatural God is useful to the sick person, can a non-theistic sick person’s prayer for himself be useful? I suppose it can – in the same way that disputation with oneself can be useful in the healing process, I suppose prayer consciously directed towards the highest aspirations and dignity of the human spirit can be just as useful in healing oneself. But I need to think about this. Perhaps I need to pray about it too.

Wednesday, December 28, 2005

An Unwanted Journey: Day 0034 - Arguing With Yourself


Ken Wilber uses the phrase “condemned to meaning.” By this, he means simply that we have no choice; when cancer is diagnosed, we will look to the medical experts to treat the illness, but to our culture to provide the scripts by which we attach meaning to the sickness which has invaded our life. Like his wife Treya did when she was diagnosed with breast cancer, I find myself alternating, sometimes at the speed of light, between the various scripts provided by Christian, New Age, Medical, Psychological, Gnostic, Existential, Magical, Buddhist, and Scientific approaches to the meaning of cancer (see yesterday’s blog for more about the idea of scripts).

If you’ve glanced through the brief summaries of these different approaches, you will probably find, like me, that not a single one is sufficient, although it is safe to say that some resonate more than others. Perhaps you find that it’s something like combination chemotherapy; if you mix a few together you can find a cocktail that is more appealing than any of the single approaches. For me, that mix would probably be a blend of scientific, medical, existential, and Buddhist approaches.

The point is simple: the meaning of cancer is a human creation, something which necessarily involves both the individual and the community in dialogue. This conversation between the personal and the communal is a non-stop process even when the voices we hear are not spoken aloud but inaudibly spoken in our minds as we think about cancer.

“What did I do to deserve this?”

“You were a shit disturber, weren’t you? That’s why you’ve got colorectal cancer now.”

“If I think positively, will that extend my life?”

“Only if you’re an idiot who thinks wishing for things will make it so.”

“If cancer has no meaning, can’t I just make it up? If it works for me, what difference would it make for anyone else?”

“Yeah, stupid. You have a family, right? Don’t you have an obligation to at least come up with a meaning that works for them too?”

We all have these conversations with ourselves, sometimes endlessly so. If somebody else were to offer questions or opinions to us, we would feel justified in disputing their assumptions or their logic. But sometimes when the voice arises within, we feel that it must be true, it must be our authentic self. The truth is, the nonsense we use in our internal dialogues is often just as nonsensical as what we hear other people saying.

Martin Seligman, in his book Authentic Happiness, offers advice on how to argue with yourself. What I find fascinating about his advice is that he recommends we do whatever is necessary to find an optimistic meaning. In the context of coping with cancer, this means that we need to develop facility in recognizing when our internal voices are offering pessimistic interpretations. Then, once recognized, we need to learn to dispute those voices. We do so through four approaches: evidence, alternatives, implications, and usefulness.

Evidence means that often the best way to dispute the pessimistic view of cancer which is voiced internally is to show that it is factually incorrect. For example, even thought Stage III rectal cancer prognosis statistics state that 55-60% will survive after five years from diagnosis, a pessimistic view suggests that means I have a 40-45% chance of dying in the next few years. Evidence suggests that the statistics are skewed. Most involve all age groups, not guys in the early 50s with an otherwise good state of health and no prior hospitalization, with an absolutely top-notch medical team using the most current surgical, systemic, and radiation therapy approach. The evidence clearly suggests that my Stage III rectal cancer has better survival prognosis.

Alternatives means that there are other ways to talk about and look at the circumstances facing us than the often most pessimistic view we take. If we focus on the elements that are changeable (I can exercise and eat well and develop my enduring happiness levels), specific (yes, the tumour has penetrated through the rectal wall, but all the distant organs look normal), and nonpersonal (this cancer isn’t about me failing in some way; it’s just an unfortunate series of events; and, after all, we’ve caught it before any evidence of metastasis), then those alternatives become life-enhancing and productive.

Implications means that even if the evidence is stacked against you, even if reality looks grim, we can still decatastrophize. What are the implications of Stage III rectal cancer? Well, we simply choose those that are life-affirming and ignore the worst-case scenario.

Usefulness means that sometimes the only smart thing to do is evaluate whether holding a belief about your prognosis is destructive or not. Whether it is accurate or not may matter far less than how it helps you. No, the world may not be fair, but the smart person will not think about that. If you concentrate instead on what you can do to make things better, things will be better.

Tuesday, December 27, 2005

An Unwanted Journey: Day 0033 - Script Runner


If you’ve ever programmed a computer or been responsible for updating databases, you’ll understand all about scripts. One variety of script is the SQL script (structured query language) in which a series of instructions are carried out against tables, views, fields, indices, and relations.

Today, for instance, I spent my time sequestered in a concrete bunker we call the data centre running update scripts against our ERP (enterprise resource planning) database in Oracle. The longest of these scripts ran for about 2 hours. Its purpose in life is to ensure that the entire database is modified so that it will accept new data generated by the Delphi 7 software application which powers our ERP system. When the users of our ERP system come back January 2nd, they will find new features and functions available to them provided by both software and database modifications both of which are generated by scripts.

Scripts can be easily corrupted. Misspell one word or move one line into the wrong location and the entire database or application can collapse into a heap of meaningless bits and bytes.

Cancer is something like that. At the biochemical level of our existence (in fact, all life), DNA scripts can become corrupted, thereby shattering the patterns which sustain life. Medical science has made great strides in treating cancer through blunt force methods like chemotherapy, radiation therapy and surgery. But it hasn’t helped as much in explaining how these script errors are introduced into DNA in the first place or in preventing such errors. In that regard, it is still very much like computer programming and database engineering – any attempt to fix errors in scripting can easily backfire, generating other unacceptable problems.

Cancer as an illness is all about scientific knowledge; it’s like software as the product of database engineering and programming constructs. Cancer as a sickness, however, is about the cultural meaning we assign to the experience of having cancer. In this regard, it is like software experienced by users who see only the forms, reports and menus. For them, the meaning of a software application is provided by their job description and the keystrokes or mouse clicks in the application which help them do their job. The less the user knows about the underlying programming and database constructs, the more the meaning of that application becomes the product of their own scripts, the meaning they assign to the experience of the software.

Cancer as a sickness is vastly more important to the patient than cancer as an illness. In fact, cancer as a sickness is much more significant to everyone, medical practitioner and patient alike, than cancer as an illness. There are still scripts for cancer as sickness (cultural meaning), just as there are scripts for cancer as illness (DNA). We may have options available to us in the scripts we run as we try to determine the meaning of cancer, just as the meaning of a software application varies according to the job description of the user. But, I would argue, we have to be very vigilant about the scripts we choose to run in providing meaning for the sickness of cancer.

What are some of the scripts available to us (what follows derives from Ken Wilber’s Grace and Grit, p46-7)?

  • Christian: cancer is a punishment from God for some sort of sin

  • New Age: cancer is a lesson; you have given yourself cancer and now need to learn something about mistakes you have made in the past

  • Medical: cancer is a biophysical disorder; psychological and behavioural approaches are ineffectual

  • Psychological: cancer is repressed emotion, perhaps even a death wish

  • Gnostic: cancer is an illusion; when you awaken from the illusion, the cancer will be gone

  • Existential: cancer has no meaning; whatever meaning I give it is the only meaning that matters

  • Magical: cancer is retribution for bad thoughts and feelings about other people

  • Buddhist: cancer is an inescapable part of the manifest world; only in enlightenment is it possible to transcend the impermanence of all manifest existence

  • Scientific: cancer is the effect of either a single or a cluster of causes; some causes are determined, others occur by chance; either way, there is no meaning, only chance or necessity

Coping with cancer is mainly about running scripts to discover the meaning of the sickness. If it was just about treating the illness of cancer…well, then my blog entries would be far fewer in number. As it is, I am a script runner, trying to learn what I can about the illness and doing what I can to create meaning about the sickness.

Sunday, December 25, 2005

An Unwanted Journey: Day 0031 - Christmas Cancer


It’s Christmas. And yet the first thought of the day is not Christmas cheer, stockings, turkey, or presents…it is CANCER!

Last night, my wife, my eldest son and I (my youngest son decided church wasn’t where he wanted to be) went to our local Anglican church for the Christmas Eve eucharist. We went mainly because it is something we traditionally do; I went chiefly because I didn’t want to be the humbug who said “No”, but also because I wanted to see my friends in the choir, especially one person who told us at Thursday’s choir practice that they have found something in her breast that requires a biopsy as soon as possible. I spoke to her, a nurse in the choir, and my naturopath before taking my seat in the congregation alongside my family and all the others ready to sing the carols we all love.

But the word hangs in the air – CANCER – my cancer is already diagnosed and ready for battle. Her diagnosis, we hope, will be different; the surgeon and pathologist will discover it is nothing more than a benign growth. That would definitely be the best way to end 2005.

****

Last night, as another part of our home-grown tradition, we read one of our many Christmas books. It is a tradition which owes its origins to my wife’s family. Her father would read The Littlest Angel every year. If you’ve never read this story, it is well worth the effort of finding a copy. The most memorable reading for me, as I gradually wormed my way into their family over the years of dating and then being married to their daughter, was the Christmas of 1988. Father was in his hospital bed and we were gathered around him. He couldn’t read the story, so I agreed to do the reading on his behalf. The story speaks of all the good things of our life, the beauty of nature, the gifts of creation, the wonder of childhood. The words caught in my throat a couple times, but I managed to get through it all. Father died a week before my youngest son was born.

Last night, the atmosphere was more cheerful, buoyed by gratitude and thanksgiving that we have one another and our traditions to keep us warm. We read A Wish for Wings That Work, each person taking turns reading a couple pages and showing the fantastic illustrations to everyone gathered by our Christmas tree. Like The Littlest Angel, the lesson was simple: we are at our best when we take our strengths and use them in the service of other people instead of wishing for things that can never be. I love these simple lessons. To me personally, they are so much more relevant than a recitation of the Nicene Creed.

****

Today, we will revel in each other’s company, receiving and making calls to relatives, maybe watching some of our new DVDs or listening to our new CDs; I will watch Kobe Bryant and Shaquille O’Neal square off as the Lakers fight the Heat and maybe even catch some of the San Antonio/Detroit game. My wife tells me that I will definitely be helping with meals ;>)
But behind everything, there is that word again – cancer. It will not cancel Christmas for us. It will simply tug at our sleeves throughout the day, reminding us that nothing can be taken for granted. Maybe that is the strange gift this word brings to us today.

Saturday, December 24, 2005

An Unwanted Journey: Day 0030 - Pay It Forward


My youngest son and I experienced the crazed, frenetic pace of last-minute Christmas shoppers in their cars today, some of them driving without any consideration at all for pedestrians or other drivers. We, too, were out doing some stocking-stuffer shopping before the crowds were too thick and cursing the rude and ridiculous alike as we struggled simply to get in and out of mall parking lots. But then, in an almost Dickensian moment, a kind of Scrooge-gets-Christmas episode, we experienced first-hand something which Catherine Ryan Hyde called Pay It Forward.

We had promised to buy tins of Tim Horton’s decaffeinated coffee and hot chocolate. The line-up of cars was one of the longest we’d ever seen. But there was one driver who had obviously made a mistake and not found the end of the line. He was waiting patiently but probably hopelessly for someone to let him into the line-up. On a whim, I motioned for him to cut in before us. Then, when we finally got to the window to pay for our tins, the clerk told us that the gentleman in the car ahead of us had already paid for our order simply because he appreciated us letting him into the line.

A little while later, while getting breakfast in another drive-through, we decided to “Pay It Forward” for the person in the car behind us in the line-up. We didn’t see if the driver was as pleasantly surprised as we had been. In both cases, what we experienced was rather mundane, simple examples of actions which were “beyond ego”, a kind of affirmation not of the triteness of Christmas spirit, but of something more akin to “hey, we’re all in this together.” It was, however, a transitory moment.

Later, as the day progressed, I fell back into a funk that was totally dependent on ego. Yesterday, as we spoke with the radiation oncologist, I asked about possible side-effects of radiation on sexual function. The answer I received was that, although the radiation might not have much effect, the surgery would probably do long-term damage to sexual function by damaging nerves. Last night and again throughout most of this day before Christmas, I wallowed in self-pity with ego-driven thoughts of myself, the “guy who might never have another erection.”

There really isn’t anything wrong with grieving loss of sexual function…nothing at all. But when the ego pushes aside truly transcendent moments which come from a place beyond ego, then we need to do something about that. Ego is good. Ego is fine…in its place. Cancer is bad. Cancer sucks. But neither ego nor cancer is the real point of the journey, after all. Pay It Forward moments remind us that not only are we all in this thing together, but that the tragedy of cancer is, in its own way, an opportunity to move beyond ego. I hope I can remember this lesson.

Friday, December 23, 2005

An Unwanted Journey: Day 0029 - Radiation Oncology


I coached his son and my son in basketball two years ago. As soon as the radiation oncologist walked into the consultation room to join my wife and me, we both recognized each other but couldn’t quite recall the connection until a little later when my wife broke the ice and asked about a few possibilities. We settled on basketball almost immediately. It feels good to know that my radiation oncologist has a personal connection with my family, even though it’s somewhat tenuous.

Today, as you may have figured out by now, we went to the Grand River Regional Cancer Centre where we reviewed how the radiation therapy would be conducted. I’ll go back to the centre in the first week of January for a simulation session in which we use a CT scan reserved just for the radiation oncology team. During that session, we will discover exactly how I will be positioned for a course of 28 fractions of radiation therapy. Permanent tattoos in the form of small, bluish dots will “mark the spot” to guide subsequent radiation therapists as they set me up for the daily, Monday-to-Friday sessions beginning January 9th for a little over 5 weeks. After that, I will have about a 6-week break to recover, followed by surgery.

We talked about side effects, the purpose of the therapy (reduce the tumour for excision and to make possible a low anterior resection), how I might feel, and how the chemotherapy side effects might interact with the radiation therapy side effects. To make it short and sweet, there may be about 3 weeks in which the side effects of radiotherapy will grow increasingly worse, followed by another 3 weeks after the treatments have stopped when I will gradually feel better. That will be followed by a 2-week period that we’re calling the “honeymoon” when I shouldn’t feel too bad at all – then, it’s surgery.

There will be some damage to the skin in the pelvis, some possible inflammation of the bladder and prostate, and probably a fair amount of fatigue. It may even be that I won’t be able to work for a few weeks prior to surgery.

Before the consultation, I went to medical imaging for some chest X-rays. After the consultation, we met with a volunteer to get enrolled in an orientation session called “Feeling Your Best During Cancer Therapy” for next Friday about coping with chemotherapy.

We also picked up an Outpatient Oncology parking permit and got our instructions and activation key for the online My CARE Source. Back at home, after activating my site, I was pleased to see a discussion board, web links, a place to store questions, as well as a my health area where I could document all of the following:
  • My Conditions

  • My Treatment

  • My Side Effects and Self Monitoring

  • My Appointments

  • My Medications

  • My Care Team

  • My Diary

  • My Profile

  • My Community Resources

  • My Education

I am really impressed with what I’ve seen of the GRRCC and its team members. And they’re all working for me!

Thursday, December 22, 2005

An Unwanted Journey: Day 0028 - Spirituality


Concentrating on the objective realities, the physical “stuff” of cancer and cancer treatment comes naturally to me. I crave information as a first line of defence in coping with cancer.

Why is this true for me? I don’t know. It could be a gender tendency as one of my friends proposed. Guys don’t want to talk the cancer out, as some women seem to do, they want to dig it out and the sooner the better. “Get me a knife and some bandages and I’ll be fine” seems to be the stereotype for male approaches to coping with cancer. But you can’t make the incision until you have the precise information you need to take action.

It may be because of the nature of the work I do. Information and technology and management of problems – well, cancer’s just another problem to be managed through good information and judicious use of technology – maybe.

Or it may be because I’m not a member of Alcoholics Anonymous and don’t say the Serenity Prayer every week at meetings.

It could be because I don’t believe in God…or to be more precise…I don’t believe in theistic Christianity. I have no problems intellectually with non-theistic interpretations of any major world religion. But the key here is “non-theistic”. You can’t pray to a God who doesn’t exist! And you certainly can’t find comfort in a basket load of Bible verses whose underlying assumption is that some divine personality is overseeing and possibly intervening in human life, even to the cellular level that is the turf of cancer.

On the other hand, I understand why people pray for me and I greatly appreciate the sentiments and generosity that implies. It’s just not for me personally. I’m not praying about my cancer. I’m not asking God to make everything better or even to give me the grace to cope with whatever comes my way. Others can do that on my behalf if they want. But it makes no sense for me to pretend that I believe in a God who intervenes.

Spirit, on yet another hand, is something else entirely – ultimate concern, the god beyond God, “God as a verb” – these all have a great deal of potential both intellectually and emotionally for me.

This attitude of mine is, I have discovered, not a common response or coping mechanism when the diagnosis of cancer has been made. Over 90% of adults believe in God and over 70% say religion is a very important influence in their lives. For some, a diagnosis of cancer is the occasion for the discovery of faith in the God of the Bible. I do not quibble with those for whom such thoughts are comforting. But for me it is not so, nor would I ever hope that I would change in the face of serious illness or death. As Carl Sagan put it in an essay in March 1996 before he succumbed to bone marrow disease:

"Many of them have asked me how it is possible to face death without the certainty of an afterlife. I can only say that it hasn't been a problem. With reservations about 'feeble souls,' I share the view of a hero of mine, Albert Einstein: 'I cannot conceive of a god who rewards and punishes his creatures or has a will of the kind that we experience in ourselves. Neither can I--nor would I want to--conceive of an individual that survives his physical death. Let feeble souls, from fear or absurd egotism, cherish such thoughts. I am satisfied with the mystery of the eternity of life and a glimpse of the marvelous structure of the existing world, together with the devoted striving to comprehend a portion, be it ever so tiny, of the Reason that manifests itself in nature.'"

“Feeble souls” isn’t how I would put it, no matter how great a man I think Albert Einstein. But Einstein, Sagan, and people like Treya Wilber are the model for how I wish to approach life, illness, and death. If you want to know what I mean, then take a couple days and read Ken Wilber’s tribute to his wife Grace and Grit: Spirituality and Healing in the Life and Death of Treya Killam Wilber.

Wednesday, December 21, 2005

An Unwanted Journey: Day 0027 - Medical Oncology


My eldest son joined me again today for another trip to Grand River Hospital. This time, instead of medical imaging, we had our very first trip to the Grand River Regional Cancer Centre. The GRRCC was able to find a cancelled appointment for Wednesday the 21st and get me in to see the Medical Director of Systemic Therapy a full month before the date offered me yesterday. This was very good news for me.

The consultation and physical examination was straight forward and went as expected…almost. I had to revise my expectations for the duration of neoadjuvant treatment. In addition, I hadn’t fully realized in my research thus far that I would also be getting adjuvant chemotherapy. Preoperative chemotherapy will be delivered 24 hours a day by ambulatory infusion pump for a full five weeks and will involve low-dose 5-Fluorouracil (5-FU). Postoperative therapy will begin about 4 or 5 weeks after surgery and will likely involve a “cocktail” of drugs – either FOLFIRI (folinic acid, 5-FU, and irinotecan) or possibly FOLFOX (folinic acid, 5-FU, and oxaliplatin). For both preoperative and postoperative chemotherapy, I will have a catheter in a vein with a pump connected. Each week, I will have a nurse replenish the medicine.

There are, as you might expect, a number of precautions and possible side-effects with which I may have to deal. The most important of these, and possibly life-threatening, is a fever of 38.3 Celsius (101 Fahrenheit) at any time or 38.0 Celsius (100.4) for more than one hour. A fever may indicate a severe depletion of white blood cells.

Other side effects are what one might expect, the most feared of which for me personally is general fatigue. The GRRCC has a short seminar planned to explain the chemotherapy treatment, side effects, and how to deal with fatigue which I will attend early in the New Year. My hope is that I can manage general fatigue well enough to get substantial work done in my role as IT Manager. Although I don’t like admitting this, some of my self-esteem derives from how well I perform my job functions, a major part of which is my mental agility and energy levels.

I really do appreciate and am grateful for the progress being made on treating my cancer. But now that I am so close to actual initiation of chemoradiotherapy, the impact is becoming less theoretical and more real. Today was, emotionally, one of highs and lows – highs because of getting this appointment, our annual company Christmas party at King Crab Oyster Bar & Grill (which was absolutely fantastic, by the way!), going to see a Vinyl CafĂ© Christmas with Stuart MacLean at the Center in the Square with my family, and lows because of the realization of what I and my family are going to be going through very, very soon.

Tuesday, December 20, 2005

An Unwanted Journey: Day 0026 - Special Ordinary


Apart from barely being able to walk down the stairs or to bend down to pick something up off the floor, it was a very good day. But even those aches and pains felt good. They were the telltale symptoms of a good physical workout, the result of barbell and stability ball squats, indicators that the core training exercises from yesterday were already paying dividends.

But what set this day apart for me was simply that cancer wasn’t always on my mind. Knowing approximately what the staging is for my cancer, what kind of treatment I can expect, having appointments scheduled to meet with the radiation oncologist and medical oncologist – that was enough to relieve my mind sufficiently to turn to other matters with more enthusiasm than I’ve been able to muster over the past three weeks.

Friends and some family members have also been incredibly generous. Our children’s god parents and cousin came to visit yesterday and to demonstrate their love and concern for the entire family. College friends, online buddies from around the globe, fellow choristers and parishioners, my sister’s husband – they have all been very supportive and generous in their offers of assistance.

But what really makes a good day great is the people closest to me, my wife and my sons. Throughout the past three weeks, they have made the uncertainty tolerable. Good days and bad days only make sense with them in the centre of everything. Between the four of us (not to mention our cat and dog), we have created something that transcends good news, bad news, and no news at all.

Monday, December 19, 2005

An Unwanted Journey: Day 0025 - Wait Times


Wait times are on the political agenda these days. The Ontario government has a Wait Time Strategy to reduce wait times for key medical services. Cancer surgery and diagnostic scans (MRI and CT) are two of the five services being targeted by the provincial government (the others are cardiac procedures, cataract surgery, and joint replacement). Unfortunately, it won’t be until December 2006 that the Wait Times Information System will be available in 50 Ontario hospitals.

In my case, I am not disappointed with the wait times for diagnostic scans at the Grand River Hospital (from the time of my first meeting with the surgical oncologist to the time of the CT scan was 10 days, 14 days to wait for the MRI). But, if the wait times listed on the Grand River Regional Cancer Centre’s site for chemotherapy and radiation therapy are reasonably accurate (they use the median time from a referral to the centre to the first treatment), then I will have to wait 5 weeks from December 14th (the day after the tumour board made its decision about the treatment protocol to be followed for my case) until treatment starts. That would be January 18th. Then, surgery would be exactly 12 weeks later on April 12th.

Comparison of wait times among the province’s regional cancer centres is done using data forwarded from each centre to Cancer Care Ontario. The GRRCC hasn’t yet posted its cancer surgery wait times on its own site, although there is a link on Cancer Care Ontario’s site where you can select Wait Times in Your Area which then takes you to the waittimes.net site where you can search for wait times by the category of cancer and location of hospital. That search engine told me that the median wait time for gastroenterological cancer surgery at Grand River Hospital was a median of 18 days, an average of 26 days, and 90% completed within 61 days. The times are calculated from the patient’s decision to proceed with surgery to the time when surgery is complete.

Rectal cancer that is treated preoperatively with chemotherapy and radiation therapy automatically pushes the surgery out by 12 weeks, so the comparisons for me for surgical wait times don’t compare readily with the standard wait times.

The problem is more subjective anyway, no matter what the statistics and figures indicate. I was told 5 days ago that there was confirmation on the pathology report of carcinoma and that the tumour board had agreed on the treatment protocol recommended by my surgeon. I called the GRRCC today to talk to the clinical director of supportive care. She was attuned to the problem of waiting for newly diagnosed cancer patients and quite sympathetic. Although she couldn’t tell me when I would be meeting with my medical team, she promised I would receive a call tomorrow to clarify next steps.

That’s all I can really expect, I guess. If I have to wait for chemotherapy and radiation therapy, then I’ll simply have to grin and bear it. But I can use the time to research, to work on my physical training program which I started today (I can barely walk!), and even try to enjoy the Christmas season. I may even put off my diet until Christmas is over.

The other major news today included getting copies of the pathology report and the text copies of the CT scan and MRI reports. Until I meet with my medical team at GRRCC, I should be careful interpreting the technical terminology of those reports, but from what I am reading, it appears there is no evidence of metastatis to distant organs, but possible lymph node involvement in two small nodes in the mesorectum (“two small presacral adenopathies”). The tumour itself is about 6 cm long and about 1.3 cm in thickness, which means the tumour has penetrated through the rectal wall. The MRI indicated “some spiculation and irregularity on the outer surface on the rectum”. The pathology report confirms the diagnosis: “invasive colonic adenocarcinoma arising within an adenomatous polyp.”