Saturday, December 17, 2005

An Unwanted Journey: Day 0023 - You and Me


“I’m constantly hearing you have to be positive. But you can’t ‘pretty up’ this disease. You have to face it, deal with it, and you have to think about it.

When I’m faced with depression, sleeplessness, anxiety, the last thing I need is a pep talk, Intellectually I know that feeling positive is good for your mental health and yes, I will get there. But for now, I need a place where I can allow myself to feel miserable, and down, and depressed, a place where I’m not protecting those around me from cancer. A place to deal with the tough issues that come with cancer.”

-Rosa McDonald, breast cancer patient (p.17 - The Emotional Facts of Life with Cancer: A Guide to Counselling and Support for Patient, Families and Friends)

I hear you, Rosa!

Well meaning people tell me to “put my brain into neutral”, “let God be in control”, “don’t think about the ‘what ifs’”, “have a manager’s state of mind”, “repeat healing scriptures twice each day aloud”, “don’t tell people anything about your cancer who don’t need to know what’s going on”, “forget the technical information research”, and the grand daddy of them all – “just live one day at a time”. On the other side of the hill, a fellow cancer survivor suggested we go out to one of his favourite haunts, drink a few mugs of beer, get into a fight, and flirt with the women on “ladies night”.

I appreciate all these people. I really do. Some of them are among the most important people in my life and always will be. They’re all trying (in both senses of the word) to be supportive and demonstrate their concern for my wellbeing. But they’re missing something terribly important that I think I need to express. And sometimes I feel like I need to shout it from the rooftops:

“I hate this f…ing cancer! I hate what it’s done to my life, to my plans, to my self esteem, to my hopes and dreams, to my sense of control. I feel betrayed. I need to understand what’s going on, why it’s happening, what to expect next…”

OK. I’ve said it. And I realize that if it wasn’t cancer it would be something else. But it is cancer!

****

As I read through the material the Colorectal Cancer Association of Canada so graciously sent to me recently, I came across a wonderful booklet entitled The Emotional Facts of Life with Cancer: A Guide to Counselling and Support for Patient, Families and Friends. It is a publication of the Canadian Association of Psychosocial Oncology whose first edition was released in February 2003. An online version of the booklet is available at http://capo.ca/eng/docs/bookletREVISED.pdf.

It seems these people get it. Every cancer patient (I don’t think I should call myself a cancer survivor yet until I’ve paid my dues with treatment) is unique and the way they deal with cancer will be unique. Counsellors who get this use an approach specifically tailored to the unique needs of cancer patients - the technical term for this kind of counselling is psychosocial oncology. They recognize the informational, psychological, social, practical and financial, and spiritual needs and try not to confuse categories too often.

Like hope and concern, there is a flip side to this business of emotional needs; namely, that of caregivers, family and friends – the very people whose attempts to provide support to patients may backfire on them. Perhaps I can be bold enough to suggest to those who love me and are reading my journal:

“Take care of yourself too. I do love you, even when you say things I don’t appreciate or aren’t useful in a specific situation. You are entitled to your feelings and beliefs, to your own sense of loss and helplessness, to your own need for care and concern. I might not be able to help, but there are professionals who can. Just remember that.”

Friday, December 16, 2005

An Unwanted Journey: Day 0022 - Experience of Time


She is really an incredible person. The executive assistant for my surgical oncologist has been very supportive and helpful, responding quickly to all my questions and concerns. Perhaps the most useful asset she brings to the surgeon’s medical practice is the rapport she seems to establish so readily with troublesome patients like me. Although she is attempting to help me deal with my experience of the dragging of time, I'm not sure anyone can affect such a subjective feeling.

I am finding this period between diagnosis and confirmation of the treatment plan and the beginning of chemoradiotherapy hard to handle. The waiting period really is minimal; it just seems to drag. That’s the nature of rectal cancer diagnosis and treatment according to stories I’ve read. It seems like time isn't the classical 4th dimension any more. For some, time blurs. For others, time is like a movie that's paused and then starts up again with no recollection of what went on in the interim. For me, it simply drags when I can't get the information I think I need when I want it.

Work is therapeutic. Everyday activities help. These things distract me and help me deny that anything has changed...at least for a few moments.

It feels good to make progress with information technology problems and challenges, to meet with colleagues to review projects and plans, to joke with acquaintances about Christmas shopping and the foibles of leaders in our national election campaign, to play euchre at lunch, to sing with the choir, to drive our sons to school and basketball tournaments, to walk with my wife in the evenings with the crunch of snow beneath our feet, to relax and watch the Toronto Raptors lose a few more games, to munch on chocolates and ju jubes in the shape of Santa Claus…these everyday things truly help...momentarily.

But…my experience of time and my interests have been transformed. Thinking three months down the road towards surgery takes a supreme effort. Subjects that would have elicited my ready attention before have just faded into a muted background. I could care less about politics these days. International affairs - it barely registers on the radar. Even technical issues pertinent to my work have been sidelined. I know this will change. I just don’t know when.

When I can pick up a novel again instead of a book on colorectal cancer in the evening, I’ll know time is returning to normal.

Thursday, December 15, 2005

An Unwanted Journey: Day 0021 - Questions


Is it possible to get through a day without more questions?

What is the preoperative staging assigned to my case? What TNM (tumour/node/metastasis) classification has the tumour board given me (see below)? What’s my activation key for My CARE Source, the Grand River Regional Cancer Centre’s online resource for managing my treatment plan? What is the significance of clinical complete and clinical partial responders to neoadjuvant chemoradiation for rectal cancer? And what exactly is the difference between clinical responders and pathologic responders? Perhaps even more importantly, is there any point to the patient looking for and expecting answers to these kinds of questions?

***
TNM Staging System
Tumor

  1. T1: Tumor invades submucosa.

  2. T2: Tumor invades muscularis propria.

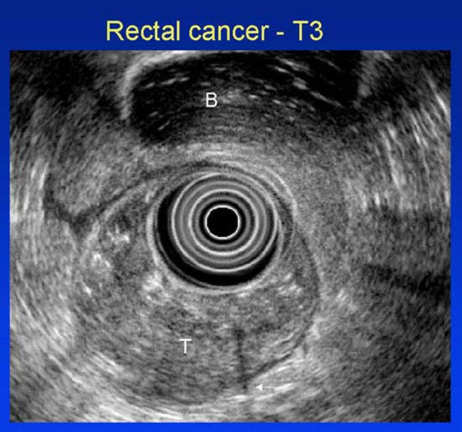
  3. T3: Tumor invades through the muscularis propria into the subserosa, or into the perirectal tissues.

  4. T4: Tumor directly invades other organs or structures, and/or perforates.
Nodes

  1. N0: No regional lymph node metastasis.

  2. N1: Metastasis in 1 to 3 regional lymph nodes.

  3. N2: Metastasis in 4 or more regional lymph nodes.
Metastasis

  1. M0: No distant metastasis.

  2. M1: Distant metastasis present.
Stage Groupings

  1. Stage 1 - T1 N0 M0; T2 N0 M0

  2. Stage 2 - T3 N0 M0; T4 N0 M0

  3. Stage 3 - any T, N1-2, M0

  4. Stage 4 - any T, any N, M1
***
I feel like I’m being tossed around, not by anybody in particular, but mainly by what I should or should not do in participating in my own treatment.

In my profession, one thing that is very clear is that there is no lack of questions to ask. There are literally dozens of tasks that can be done each and every day related to managing information technology, usually organized according to the questions being asked. The trick is not in having a lot of questions; the trick is in asking the right questions at the right time with the right goal in mind. Success is more about assessing priorities and clarifying objectives than in having immediate answers to those pressing questions.

But now I feel like I’m a novice all over again. I have no idea what the right questions are or even what my focus should be.

Question: Is this normal?

Question: Would it make more sense for me to leave the technical questions to the experts and concentrate on my emotional health and general wellbeing? Or is it silly to try to distinguish between the two?

Final question for today: Is it time to put my brain into neutral yet again?

Wednesday, December 14, 2005

An Unwanted Journey: Day 0020 - Tumour Board


“The tumour board met last night to review your case. They have concurred with the diagnosis and treatment being recommended. Your name has been forwarded to the Grand River Regional Cancer Centre and you will be registered with them. Either the medical oncologist or the radiation oncologist will call me soon with the date and time for your next consultation. When you meet, the oncologist will discuss the chemoradiotherapy schedule with you and review the reports and images that helped the board make its decision last night. If you have any questions at all, please don’t hesitate to call.”

As it turned out, I was digging in my winter clothing trying to retrieve my cell phone and missed the call. I called back right away and discovered that the second set of biopsies was unequivocal. I do have carcinoma, as expected. But I qualify for the treatment protocol recommended by my surgical oncologist and can expect to get started right away with radiation therapy and low-dose chemotherapy to shrink the tumour.

This time I was prepared; in fact, I was downright cheery. Yes, I have a cancerous tumour in the rectum, but we have a good plan in place, an excellent medical team, fantastic medical resources, a loving family, dear friends, supportive acquaintances and colleagues, a good medical leave benefit package, a fitness trainer and a core training fitness program ready to go, and a determination to remain optimistic and enthusiastic about my small part in this fight.

There are so many people helping me right now. Books, movies, web sites, programs – friends and family are making recommendations and getting involved. They’re in my corner and ready to cheer me on. One friend from my college years wrote today to tell me of her fight against a Stage IV cancer diagnosis from several years ago. She is now cancer free. Her message was simple and dramatic - nobody can say for sure what will happen or fail to happen. But when you are surrounded with hope and when you are kind to other people, you can participate in your own healing. In addition, she and her family are praying for me and I know she will be there if I need a word of encouragement.

I will be training both physically and emotionally during the next three months as I prepare for surgery. We worked on the physical training program today at Popeye’s Gym. I’m excited about working out and being monitored closely as to my physical progress.

But how does one train the emotions? Well, apparently it’s not just a matter of willpower, of fighting negative thoughts and ruminations, of trying to be cheerful all the time, or even of avoiding stressful situations and people. You can actually build your enduring level of happiness through a scientifically tested regimen and clinically tested set of practices.

Two days ago, I mentioned Martin Seligman’s Learned Optimism. Yesterday, I discovered, purchased and downloaded an e-book edition of one of his more recent books about a movement he has pioneered called Positive Psychology. The book is entitled Authentic Happiness: Using the New Positive Psychology to Realize Your Potential for Lasting Fulfillment. This book has an interesting equation: H = S + C + V which translates into Happiness (enduring level of happiness) = set range + circumstances of your life + factors under your voluntary control. What this clearly implies is that even though I might not readily change my set range of emotions and can probably do little to change the circumstances in my life, I can modify factors under my control and thereby increase my enduring level of happiness. If happiness heals, then I can train myself in emotional healing.

Now, if we can just get the washing machine fixed ;>)

Tuesday, December 13, 2005

An Unwanted Journey: Day 0019 - Magnetic Symphony


I watched the first episode of the new Canadian television series Terminal City last night. My wife wasn’t sure I should watch it, but I did. It is a ten-part series dealing with one family’s confrontation with cancer. In that episode, Katie Sampson discovers she has breast cancer. The next day she takes her daughter with her to the clinic where her biopsy is performed.

Ironically, my eldest son came with me today as I ventured to Grand River Hospital for my MRI, presumably a major piece of the puzzle considered by the tumour board which meets to review my treatment options this evening. The board will have in hand the CT scan, the images from the MRI, as well as the biopsy results from last week and all the other colonoscopy and sigmoidoscopy reports. But I won’t be there. In fact, it may be next week before I meet again with the surgical oncologist to hear what the board has determined is the best way to address my rectal cancer. While I wait, they deliberate.

The MRI itself was painless. There was an intravenous, as there was for the CT scan, and there were problems yet again finding a good vein in my arm, but the procedure was straight forward. The procedure was forty minutes of keeping very still and listening to what I call a “magnetic symphony”. Even with ear plugs and a face cloth across my forehead and eyes, the sensation of the magnetic resonances, each with a distinctive tonality and rhythm, was enough to keep me in a kind of limbo state, close to sleep, but still aware. I was a little concerned that I might move my body as the images in that near-sleep state kept floating through consciousness.

Again, like the CT scan, we stopped about half-way through the procedure for a contrast injection to illuminate the vascular system in the pelvic region. The only awkward thing from the patient perspective about the whole procedure was the length of time required. But from the little I have learned about the technology, the time required is well compensated. The MRI images can be highly tuned to answer precise questions that the medical team has regarding an injury or condition.

Now, I have a few questions that need to be answered too!

Monday, December 12, 2005

An Unwanted Journey: Day 0018 - Optimism


A few days ago I wrote that hope and concern were flip sides of the same coin. Another way to imagine this is to think of a spectrum with markers demarcating more or less optimistic outcomes. As I await medical imaging results and the pathology report, it is the continuum or spectrum of outcomes that drives my anxiety and my hope.

At the pessimistic end of the spectrum is the possibility that the images will reveal a tumour which has broken through the bowel walls completely, has invaded numerous lymph nodes and possibly even metastasised to the liver or lungs. The biopsies would show clear carcinoma.

At the optimistic end of the spectrum is the possibility that the images will show a large tumour that has not broken through the bowel wall, but is long and relatively shallow. The biopsies would show a tubulovillous adenoma with low-grade dysplasia like the previous biopsy. The CT scan and MRI would show no indication of lymph node involvement and no hint of metastases to any other organs.

In between, we get middling results. Perhaps the biopsies show no carcinoma, but the images show penetration of the bowel wall. Perhaps the biopsies give evidence of cancer, but the tumour is shallow with no lymph node involvement. Perhaps there is only some evidence of enlarged lymph nodes but no marks on the liver. And so on…

As I read Paul Tillich’s The Courage To Be today, I discovered that these kind of scenario-building fantasies reflect the natural inclination to relieve anxiety by turning it into fear of a particular object. In other words, generic anxiety and dread are eased by thinking of specific situations that I fear but for which I can generate a measure of courage or fortitude. By focusing on concrete objects or situations fear and bravery becomes possible. Far, far worse is unspecified, inarticulate dread. And, I suppose, it might also be reasonable to assume that unspecified, unrealistic hope is unhelpful since it betrays denial and unwillingness to face truth.

But I’m not so sure about generic optimism. Martin Seligman’s book Learned Optimism has a chapter devoted to health and the effect of learned helplessness. In case after case, he demonstrates that a “fighting spirit”, a sense of general optimism, a sense of control and participation in one’s own treatment leads to better results. Where there is a delicate balance, optimism he says can make the difference between life and death.

One thing about all this is virtually certain. It is far better to live one’s life with hope and optimism than to wallow in despair and dread.

Sunday, December 11, 2005

An Unwanted Journey: Day 0017 - Waiting


A friend wrote to me recently telling me about life-changing events in his own life. His survival and triumph was characterized by courage. Although he didn’t say it, the implication was that both he and I have resources which sometime are hidden from consciousness but that are available to us when circumstances deal us a blow.

As I read his note, it occurred to me that the concept of courage was something I hadn’t considered for a very long time. In fact, in the not-too-distant past, I have joked with my family saying, “I sure hope I never get a serious disease because I’m a wimp. I don’t think I could deal very well with life-threatening illness or a serious accident.” Never did I think then that I would face a diagnosis of colorectal cancer. Now, strangely, I am looking for and perhaps finding those hidden resources.

As I reconsider courage, my memory is bringing back material I have read many years ago. Today, for instance, being sure that somewhere in my library were books about courage that I need to reread, I searched for and found two oldies but goodies. The first is Paul Tillich’s The Courage To Be, published in 1952, the year before I was born. The second is another theologically oriented book by a major contemplative of the 20th century, Thomas Merton. The book is a collection of letters and is titled The Courage For Truth: Letters to Writers (published in 1993).

This week is about waiting. I’m waiting for an MRI. Then I will be waiting for the consultation I expect with my surgical oncologist to review the results of the biopsies from last week, the CT scan and the MRI.

There are a number of directions I could take in handling the waiting. There is distraction. For instance, I can simply go to work and do what is necessary. I’ll do that for sure. Then there is research. But I’ve already read so much that there are diminishing returns until I have further preoperative staging information available to me that nobody can provide except the oncologist. It might be smarter to take this week to reconsider what these great men of faith and thought have to say about courage.

Let’s see where that takes me.

Friday, December 09, 2005

An Unwanted Journey: Day 0015 - Lucky


“We are so lucky here. When we say you’re going to be scanned with the ‘old’ 16-slice CT scan, you’re really being scanned with a machine that’s less than a year old. In fact, we are one of the very few facilities in Ontario that has two CT scanners, a 16-slice and a 64-slice – both are less than one year old. Our waiting times have gone down dramatically. We can now process 56 patients a day.”

She was a very pleasant, personable woman who told me exactly what to expect. Thank goodness, because when the injected solution started streaming through my veins, it was only a couple seconds before I could feel the taste in my mouth, followed closely by an oddly familiar warm sensation in my groin. I’m glad she warned me about that one!

This evening, I’ve been sticking very close to the washroom because of the barium solution used to help highlight the organs in the abdominal scan. The frequency and urgency of trips surprised me. Nobody warned me about this part of the procedure.

Even though I will have to wait for the CT scan and MRI results, as well as the pathology results from the biopsy on Wednesday, I am feeling grateful today that we have such incredible medical resources in the Waterloo region. Today, because everything is so close by, I could go to work until noon, drive myself to the hospital for the medical imaging, then go back to work for another couple hours. When preoperative radiation treatment starts, it will be the same routine. If I had to drive to Hamilton, London, or Toronto, the effect on my work and home life would be far more intrusive.

Another comforting thought this evening came from the second episode of Carl Sagan’s Cosmos DVD series. As he spoke of natural selection and accidental mutations, it occurred to me that cancer is just another piece of evidence of the way evolution works. Random mutation of DNA and the cells in which the strands of life are contained is almost always maladaptive. In other words, cancer as an abnormal growth of cells can be thought of as par for the evolutionary course. The dance of death is the price we pay for the variety and richness of life.

Now, that thought in itself is not particularly comforting to somebody facing a diagnosis of rectal cancer. But what is comforting is the realization of the necessity of death and the awesome way in which life prevails. Our medical technology, our science, and our will to live – these are just some of the ways in way humanity improves the odds of natural selection dramatically. If I beat cancer, then it will be because evolution has taken another step beyond maladaptive mutation of cells. That step is really a leap, a kind of variation in the dance of death in which life carries on longer than one might expect.

Yes, we are so lucky here.

Thursday, December 08, 2005

An Unwanted Journey: Day 0014 - CT Scan


I deal with high tech everyday. In fact, my job title is IT Manager. Information technology is the game I play, and I think I’m pretty good at it. But this technology – the CT scan – leaves me almost breathless in the range of information it can potentially provide.

The body passes through a donut-shaped apparatus while lying on a moving table. A series of x-ray photographs are timed to be taken from many angles, and then the information from those images is collated and presented as if the body was sliced through the middle at the point exactly where you want to look. For abdominal images, it’s one of the very best ways to preoperatively stage colorectal cancers. The physician or radiologist can look at the image and confirm the presence of a tumour, measure its size, determine how much involvement the tumour has with other abdominal tissues, and even locate the best sites for preoperative radiation treatment for rectal cancer.

Tomorrow I have my first-ever CT scan, perhaps one of the most important photographs of me ever taken. I doubt it will be my good side…how, after all, does the abdomen say “Cheese”?

Still, I find myself anxious once again this week prior to yet another trip to the hospital. This is an image that I desperately want to reveal a tumour and only a tumour. No metastases, please! No lymph node involvement, please! No penetration of the tumour into surrounding tissues, please! Please, let it be just an ordinary image of a not-so-ordinary tumour spanning the rectum and rectosigmoid.

They say it’s good to be hopeful. Sometimes, though, I find it difficult to determine the difference between hope and concern. Wishing for a good outcome and worrying about a poor outcome seem to me to be just flip sides of the same coin, a currency about as loonie as the Canadian dollar.

What is it they say? If wishes were dollars…”

Wednesday, December 07, 2005

An Unwanted Journey: Day 0013 - Rectal Cancer


It’s like having your own personal National Geographic special!

That’s what Robin Williams is supposed to have said when he watched the video screen for his colonoscopy. I can’t say if the story is apocryphal or not, but now I know what he means. Today, I was admitted to the day surgery department of St. Mary’s Hospital in Kitchener where I had both a flexible and rigid sigmoidoscopy. This time I was given a choice, so I opted not to be sedated but to watch the events unfold on the video screen, including the excising of two biopsy specimens.

The objective of the sigmoidoscopy was twofold: first, to measure the distance from the anal verge to the distal point of the tumour (11 cm); second, to obtain another biopsy to confirm carcinoma, something which the first biopsy sample was unable to do. Now that the surgical oncologist has the measurements confirmed, I am an eligible candidate for preoperative (neoadjuvant) chemoradiotherapy treatments before surgery to remove the tumour.

Friday, I have a CT scan and then next Tuesday I have an MRI. Both of these are to help determine whether there is any lymph node involvement as well as get a better estimate of the size of the tumour and whether or not it has penetrated through the rectal wall into the abdomen. The chemoradiotherapy will then attempt to shrink the tumour. Surgery will use the total mesorectal excision technique to remove completely the mesorectum surrounding the part of the rectum to be excised. I won’t know for sure about whether or not a colostomy will be required until the time of the actual surgery, although the TME technique offers not only hope for a lower recurrence rate of cancer in the bowel but a greater chance to preserve sphincter control, nerve preservation and sexual function. TME is not as widespread in North America as it is in Europe. Brigham and Women’s Hospital has an archived webcast of a total mesorectal excision.

So, I guess my journey is really just beginning – a journey and a fight against rectal cancer. I trust Dr. C. Everett Koop, former U.S. Surgeon General, was right when he said, “The best prescription is knowledge.” All I really know now is the diagnosis and the treatment protocol. But this National Geographic special has really just begun.

Tuesday, December 06, 2005

An Unwanted Journey: Day 0012 - Anxiety


Anxiety is systemic.

It’s an interesting idea. And not just academically interesting – interesting in a theoretical, dispassionate sense of the word. It’s interesting in the sense of timely and appropriate to the circumstances.

At work, we have a consultant who has been involved with our company for about a year now. I have met with this consultant three or four times discussing leadership and team building. In one of those meetings, she recommended I read a book by Jeffrey Miller entitled The Anxious Organization: Why Smart Companies Do Dumb Things. I ordered the book and it finally arrived yesterday.

As I become fatigued with constantly reading about colorectal cancer, the arrival of this book provided a welcome diversion. Ironically, though, the thesis of the book seems entirely pertinent to the situation in which my family and I find ourselves – we’re anxious - anxious about my health, anxious about our finances, anxious about how each of us in the immediate family is coping, anxious about our dear friends whose father just died early in the morning…anxious.

Systemic implies something that affects the entire organism or organization. Even a single person's anxiety can be considered systemic in the context of the entire organization. In that sense, anxiety is contagious or infectious. But the author’s contention is that this pattern of contagion can be interrupted. In other words, one person, making what appears to be a minor change, can affect the entire organization, for good or ill, whether that organization is a corporation or a family. If one person in the family is overly anxious, the entire family's level of anxiety increases, and as it does, it becomes increasingly dysfunctional.

I can see that first-hand in my family’s response to the diagnosis of cancer. Tonight, for instance, as I prepare for the next biopsy and sigmoidoscopy tomorrow, I’m feeling anxious, irritable, and less likely to be a positive influence on our family.

But here’s the really cool thing about what Miller has to say about the feelings of anxiety. They are not the real me! Miller says, “We discover our true selves when we make calm, clear, and conscious choices.” That’s not to deny feelings, just to put them in their proper place.

Miller argues that thinking carefully is one of the best ways to overcome the automatic pilot of anxiety and the evolutionary dead-ends into which anxiety-driven reactions lead us. Anxiety is still important, but the automatic responses and reactions coming from our "lizard" brain, and even the "mammalian" emotional brain, do not represent the best of our evolutionary heritage. The real me responds to anxiety with recognition of the causes of anxiety, with acknowledgement of the fight, freeze, or flee response mechanism, and with gentle appreciation for the complexity and authenticity of emotional responses.

Although it is easy for us to discount the reptilian brain's meagre list of reactions, it is far harder for us to recognize the limitations of the mammalian brain's massively complex emotional responses. But that is precisely what we have to do; for once we recognize that so many of our emotional responses are habitual and based on childhood or adulescent behaviour patterns (the way we always respond), we find that we have other resources. We have choices.

It is the next step, where we marshall the resources of our neo-cortex, where we analyze, synthesize, and carefully discover what we really think, where we recall what our true principles are - it is then that we are in tune with our real nature. This is not to deny what people of faith refer to as God. It is not to toss aside prayer, contemplation, meditation, or even active listening to other people. It is simply to say that the best of me is all of me - but the command centre is the thinking brain.

Monday, December 05, 2005

An Unwanted Journey: Day 0011 - Screening


In the past few days, I’ve had conversations with many friends and acquaintances. Some are quite interested in learning more about how colorectal cancer is diagnosed. Most are amazed and somewhat dismayed to learn just how pervasive a problem colorectal cancer is in Canada.

When we get past the initial discomfort people have with talking about bowels and symptoms, I find that almost everyone is willing to spend a few minutes learning about risk factors and signs and symptoms. But not everyone! So, for those who would rather read about it than talk about it, here are symptoms and signs (note, however, that these same signs and symptoms can and often do mean something else entirely):

  • Change in bowel habits such as loose stools, constipation, uncomfortable bowel movements, thin stools, a feeling of incompletely emptying the bowels

  • Abdominal discomfort, including gas, pain, bloating, cramping and fullness

  • Bleeding (bright red or dark)

  • Fatigue

  • Weight loss

  • Iron deficiency

  • Anemia

Although I think it is important for people to realize what the signs and symptoms are, the bottom line is that we can’t wait for symptoms. Screening before symptoms arise, especially the colonoscopy, is what will make a difference in preventing unnecessary death from colorectal cancer. I just have to hope that family, friends, and acquaintances will learn from my experience and take screening seriously.

Sunday, December 04, 2005

An Unwanted Journey: Day 0010 - National Disgrace


The International Agency for Research on Cancer (IARC) has indicated that bowel cancer kills half a million people worldwide each year. In Canada, we are told that 8,400 will die in 2005 from colorectal cancer and 19,600 will be newly diagnosed. I am one of those 19,600 people. I sincerely hope I will never be one of the 8,400 in any year! But the Canadian figures clearly show that Canada has one of the highest rates of colorectal cancer in the world.

What is most depressing about these statistics is that Canada has no population-based programs designed to screen for colorectal cancer. It’s not that nobody cares. It’s simply that we don’t have government sponsored health care policies in place designed to prevent unnecessary and premature death from colorectal cancer.

In my view, one of the major weaknesses of health care policy in Canada is that it is a provincial responsibility. Now that we are engaged in another federal election campaign, the one health care initiative from the governing Liberals designed to reduce wait times for medical procedures on a nation-wide basis will now be put aside until after January 23rd, 2006. I think that initiative is incredibly important, not just to reduce wait times, but to step up national awareness that some things are too important to be left to provincial governments.

Screening for colorectal cancer could be another federal initiative. Why not? Death from colorectal cancer is an unmitigated national tragedy that is almost completely avoidable, but the provincial governments have shown no leadership on this issue at all.

The Colorectal Cancer Association of Canada has recently started its first advocacy campaign. The goal is to lobby provincial members of parliament to talk to their respective Ministers of Health requesting progress towards a population-based screening program. Here is an example of a template used for email for MPPs in Ontario:

I am writing as a constituent to ask for your support for a properly funded screening program for colorectal cancer in Ontario.

The incidence of colorectal cancer in Canada is among the highest in the world. In 2005, approximately 19,600 Canadians will be diagnosed with colorectal cancer, and about 8,400 will die of the disease. It is the second leading cause of death from cancer in this country.

If detected at an early stage, colorectal cancer can be treated effectively with a high chance of cure. We need to screen for this disease to have any hope of early detection.

In December, 2002, the National Committee on Colorectal Cancer screening announced its findings on colorectal cancer screening and recommended that screening be offered to a target population of adults aged 50 to 74 years of age, and that individuals be screened at least every two years.

While the experts tell us that screening is necessary and justified, we do not have a population-based colorectal cancer screening program in place in Ontario.

I am asking you to write to the Minister of Health in support of colorectal screening in this province. We need colorectal cancer screening.

Please consider sending an email to your provincial member of parliament. Please also consider speaking directly to those requesting your vote in the federal election campaign to request a national initiative to save lives.

Saturday, December 03, 2005

An Unwanted Journey: Day 0009 - Cosmos


I hope there aren’t a lot of sleepless nights.

This morning, my wife and I did a few typical weekend errands and then stopped to have a speciality coffee at Starbucks. Maybe it was the lack of sleep. Maybe it was having time just to be alone with her. Maybe it is the nature of facing cancer up-front-and-personal. Or maybe my body knows I need the catharsis. But when I found myself trying to explain why reading Psalm 19 in unison at the healing liturgy on Wednesday morning left me close to tears, I felt the tears welling up again.

We got in the car, drove on, and yet the tears continued unabated.

Psalm 19: 1-6

The heavens declare the glory of God; the skies proclaim the work of his hands. Day after day they pour forth speech; night after night they display knowledge. There is no speech or language where their voice is not heard. Their voice goes out into all the earth, their words to the ends of the world. In the heavens he has pitched a tent for the sun, which is like a bridegroom coming forth from his pavilion, like a champion rejoicing to run his course. It rises at one end of the heavens and makes its circuit to the other; nothing is hidden from its heat.

Gradually, I tried to explain that it isn’t the traditional Christian theology that affects me. It is what Paul Tillich would call “ultimate concern”. Being in the healing liturgy and speaking the psalm revealed something to me - as I face mortality and try to clarify values, two elements keep surfacing.

One is family and friends. Over the past week or so, family members and friends have expressed heartfelt sympathy and compassion. Their love has touched me deeply.

The other is the universe itself, what Carl Sagan would call the Cosmos. Moments of astonishment and awe occur with regularity whenever I contemplate the beauty, grandeur, and immensity of the “created” order. God is only my symbolic name for that ultimate reality.

I tried to explain that it wasn’t tears of sorrow that I was wiping from my eyes. Sure, there is something of a sense of potential loss. But far more significantly, my tears were what Tillich would say were a response to “a pervasive sense of joy.”

So, my wife and I made a change to our errand list, drove to the public library and found the first five episodes of Sagan’s Cosmos on DVD. I’ve started viewing the DVDs. It was a very good choice! If I can’t sleep tonight, I will know exactly what to do.

Friday, December 02, 2005

An Unwanted Journey: Day 0008 - Otherwise Healthy


“…he is a pleasant, otherwise healthy looking well nourished man.”

Hmmm, how appearances can deceive. The operative report from my gastroenterologist gives some clinical descriptions and then launches into a travelogue of the gastrointestinal tract viewed through the Olympus video colonoscope. Here’s the part that’s most pertinent:

“In the rectosigmoid between 16 to 17 cm to about 10 cm there was a large mass noted that extended over a distance of about 6 to 7 cm and involved about ½ of the circumference of the colonic lumen. It was a friable mass with areas of ulceration in the center. The distal end of the tumor seemed to be about 10 cm from the anal opening.”

“…This young man’s colonoscopy unfortunately shows a large rectosigmoid mass. He is quite a young man to have cancer at an early age.”

I think so too!

On the other hand, the first pathology report says “the biopsies show superficial fragments coming from a tubulovillous adenoma with low grade dysplasia. No invasive carcinoma is identified. However, the biopsies are superficial and sampling bias cannot be excluded.”

So, no cancer yet, but not necessarily no cancer!

Some things are becoming clearer to me now just 10 days from my colonoscopy.


  • I will probably be treated for rectal cancer.

  • I will probably have a special kind of MRI geared toward preoperative staging of the cancer.

  • I will probably be enrolled in a clinical trial of a chemoradiotherapy protocol aimed at reducing the size of the mass in order to facilitate surgery and improve quality of life for me subsequent to surgery.

  • I will probably not have full staging information for about 3 to 3.5 months from now until after the surgery is done and the postoperative pathology report is complete.

  • I am (tongue in cheek) “young, healthy looking, pleasant” and spoiling for a fight with this damned cancer!

  • If I qualify, I would seriously consider any clinical trials associated with preoperative chemoradiation for rectal cancer.

And now for something completely different…

If you enjoy the comedy routines of Bowser & Blue during the holiday season, you might enjoy the lyrics to their Working Where the Sun Don’t Shine in praise of the colorectal surgeon:

"Working Where The Sun Don't Shine" (The Colorectal Surgeon's Song)

We praise the colorectal surgeon
Misunderstood and much maligned
Slaving away in the heart of darkness
Working where the sun don't shine

Respect the colorectal surgeon
It's a calling few would crave
Lift up your hands and join us
Let's all do the finger wave

When it comes to spreading joy
There are many techniques
Some spread joy to the world
And others just spread cheeks

Some may think the cardiologist
Is their best friend
But the colorectal surgeon knows...
He'll get you in the end!

Why be a colorectal surgeon?
It's one of those mysterious things.
Is it because in that profession
There are always openings?

When I first met a colorectal surgeon
He did not quite understand;
I said, "Hey nice to meet you
But do you mind? We don't shake hands."

He sailed right through medical school
Because he was a whiz
Oh but he never thought of psychology
Though he read passages.

A doctor he wanted to be
For golf he loved to play,
But this is not quite what he meant...
By eighteen holes a day!

Praise the colorectal surgeon
Misunderstood and much maligned
Slaving away in the heart of darkness
Working where the sun don't shine!

Thursday, December 01, 2005

An Unwanted Journey: Day 0007 - Treatment Research


After combing through that highly technical article “Locally-advanced rectal cancer – a multidisciplinary approach” (the German protocol link from yesterday’s blog entry), I have a much better grasp of the rationale for the rectal tumour treatment option recommended by my surgical oncologist yesterday afternoon. Medical and scientific discoveries are moving so quickly that I had very little prior information from literature for the general public to fully appreciate why his recommendations were so different.

That delay between what the medical professional is doing and what is reported in literature for the layman was reinforced today when I received the shipment of the two books I had ordered online through Chapters.ca (Colon & Rectal Cancer: A Comprehensive Guide for Patients & Families and What Your Doctor May Not Tell You About Colorectal Cancer). Neither book even mentions total mesorectal excision or the neoadjuvant chemoradiotherapy recommended in the article and by my surgical oncologist. And not even the book The Intelligent Patient Guide to Colorectal Cancer (published this year), mentions high spatial resolution MRI or MRI lymphography. These latter images and techniques are a critical feature of the preoperative treatment for rectal cancer tumours and are already showing tangible results. Unfortunately, the results are mainly about improved local control of the tumour and reduced toxicity of chemoradiotherapy side effects; they do not yet show major differences in overall survival statistics (see the abstract of the German study). Most similar studies suggest at least improved quality of life for patients (the median age for study participants was about 63). The specialists also seem to be arguing about the cost-effectiveness of the treatment protocols.

Next Wednesday I go for a second scope test and biopsy, this time with a tool called a rigid sigmoidoscope. Instead of the gastroenterologist, it will be the surgical oncologist who performs the test. By the end of that procedure I will know whether we will be treating the tumour as rectal cancer (less than 15 cm from the anal verge) or colon cancer (more than 15 cm from the anal verge). Everything mentioned above concerns only treating the tumour as rectal cancer. Colon cancer treatment seems far simpler in comparison.

Wednesday, November 30, 2005

An Unwanted Journey: Day 0006 - Healing


Healing takes many forms. Often it has nothing to do with a cure. That’s a lesson lost on people of faith – not always, of course, because I know many people of faith for whom healing is about connectedness, not cessation of physical symptoms. But some “believers” unfortunately equate healing with evidence of supernatural occurrences.

This morning I attended a healing ceremony at our local Anglican church. Despite my initial uncertainty and hesitation, I found it strangely comforting and meaningful. There was the standard anointing with oil and prayers for healing, but there were also plenty of hugs and expressions of concern and empathy. In other words, there was healing to be found, despite any misgivings I might have about the implied theology of the religious ceremony.

Subsequently, I visited HopeSpring where yet another form of healing was evident. This time it was found with volunteers in a facility dedicated to helping patients and care givers dealing with cancer. The resource centre had some good information available, the most important of which was from the Colorectal Cancer Association of Canada. As I proceed through treatment, I’m sure the facility and its volunteers will be a good support for me and my family.

Afterwards, I was able to speak with the nurse and receptionist from my family doctor’s office when I picked up copies of my lab reports for the fecal occult blood test. They were clearly interested in my health and wellbeing and that of my family…again, evidence of another form of healing being offered in a spirit of generosity.

Finally, after picking up my wife from work, we found another form of healing in a medical consultation with my surgical oncologist. Not everyone can find healing in medical information, but I’m one of the lucky ones for whom knowledge and expertise provides comfort and direction. We left that consultation with a map which is already helping us deal with an uncertain future. Here’s what’s in store for us:

We will follow a German protocol which distinguishes between colon cancer treatment and rectal cancer treatment depending on the distance of the tumour from the anal verge. If the tumour is over 15 cm from the anal verge, then we will treat the tumour as a form of colon cancer, scheduling surgery as soon as possible. If the tumour is under 15 cm from the anal verge, then we will treat the tumour as a form of rectal cancer, scheduling an MRI immediately and then consulting with a tumour board. This board of experts will determine whether to treat the tumour with radiation therapy for three months before surgery. If they determine not to use radiation therapy, then I will likely receive a short course of chemotherapy followed by surgery.

One way or the other, I will have major surgery. The full staging of the cancer will be incomplete until the pathologist’s report following his/her examination of the excised tumour. There will also likely be postoperative radiation and chemotherapy. As the surgical oncologist said so succinctly, “Our goal is to have you cancer free not just six months from now, but five years from now.” With our plan in place and the knowledge that I am in very good hands surgically, a little more healing has occurred today.

Tuesday, November 29, 2005

An Unwanted Journey: Day 0005 - Prognosis & Performance


Parking my brain was actually quite enjoyable…for as long as I could maintain the discipline, that is – I made it through all yesterday evening, thanks to my son watching a Raptors game with me on TV. But when I awoke early, I began reading the chapter on prognosis in The Intelligent Patient Guide to Colorectal Cancer. Surprisingly enough, even though the statistics were not encouraging, the impact remained minimal for the day; perhaps that was because my brain had been in neutral for a few hours.

Here are the statistics, for what they’re worth:

  • Stage 0: 97% of patients with this stage are expected to live five years and likely be cured

  • Stage 1: 96%

  • Stage 2: 87%

  • Stage 3: 55% - 60% if one to three lymph nodes are cancerous; 33% if four or more lymph nodes are cancerous

  • Stage 4: 2% - 5%

It’s difficult concentrating at work. But when I did focus, I got quite a bit done. It was also the day in which I had my annual performance review. That went extremely well. Evidently, by concentrating on preventive measures and automated monitoring tools, by catching potential security threats quickly, by regularly installing patches to the operating system, and by upgrading the backup systems, I have had significant success in creating a powerful and stable IT environment. It was also assuring to receive very positive comments about my people and organizational skills.

I also enjoyed conversations with the parish priest, an intake worker at a local counselling agency, a neighbour who is a specialist in applied health research, a peer support person at a cancer survivor’s group, a minister friend whose wife died of cancer about seven years ago, as well as email from good friends. I really am blessed!

And now that it is evening again, I am trying once more to put my brain into neutral by watching another basketball game. Allen Iverson is truly a marvel.

Monday, November 28, 2005

An Unwanted Journey: Day 0004 - Anger & Hope


No, there was no Day 0003. Of course, there was a Sunday, and I was thinking a great deal about colorectal cancer yesterday. My parents did visit for a few hours. But the day was not one in which I found expression in writing. Instead, it was a day of anger, denial, frustration, and heartbreak as I watched the impact of my illness of one of my sons. It tore me up to witness his sense of loss and helplessness. I couldn’t find a still point in which to express the feelings for the day.

Today is different yet again. I am back to work. I certainly don’t feel very productive right now, but it’s good to tell my colleagues about what’s happening and to review projects with which I can make some progress before surgery occurs. My sick leave entitlements are better than I was anticipating. And my colleagues are generally as supportive as I have any right to expect.

Both my surgical oncologist’s receptionist and my general practitioner called today to talk about next steps. My GP informed me that my alkaline phosphatase results were reasonably good (130) back in August when my annual blood tests were performed. Elevations of alkaline phosphatase can indicate blockage in the bile ducts of the liver when metastases are present from colorectal cancer. There was no reason at the time to have my CEA (carcinoembryonic antigen) tested, but I’m sure that will occur soon. CEA is a protein which some colorectal cancers produce and can be linked to a growing tumour.

Both my GP and the surgical oncologist’s receptionist advised me to “put my brain in neutral” for the next few days until I’ve had my consultation with the surgical oncologist to review my treatment and staging options. Maybe they’re right. Maybe my research is elevating my anxiety levels unnecessarily right now.

There is a cancer support group in the Waterloo Region that offers some promising programs – HopeSpring. This resource might offer some help for our family as we try to cope with cancer. There are peer counsellors, support groups for patients and caregivers, discussion groups, classes, therapies, yoga, tai chi, and a resource centre. If I am enrolled in the Grand River Regional Cancer Centre’s CARE Source programme, then there will also be other professional supportive care options available to me and my family. I can even manage my treatment plan online using this resource.

I guess this means Day 0004 is a good day with some reason to hope and transcend the anger and frustration without denying the value of days like yesterday.

Saturday, November 26, 2005

An Unwanted Journey: Day 0002 - Too Much Life


Family, friends, and neighbours have been incredibly supportive today. You will notice that I don’t mention names of family members, friends, acquaintances, or colleagues on my web blog. That’s simply because I want to respect their privacy, not because I don’t appreciate their significance in my life.

But from the moment I got up this morning, it seemed like someone had a hug, called on the phone, shared comforting experiences, wrote supportive emails, went for a walk with me, or simply asked how I was doing. To put it simply, I felt loved and valued by those around me.

What the conversations, emails, and stories also revealed, though, was what a neighbour perceptively named “too much life”. If you give people an opportunity to share in your own story of life’s twists and turns, you will discover just how many others are either currently involved in their own difficulties or have endured traumas that put your own into context. “Too much life” is just one way of saying that sometimes life deals us hands that we would not have chosen on our own or even guessed could happen. But when we share with one another, we realize that our own little circle of concern is part of a far larger canvas of intersecting circles of concern. In those areas of overlap, we can comfort one another and learn from one another.

In most cases, all we have to do is ask. Today was just one such example of how asking and giving are reciprocal and mutually beneficial.

Still, the rollercoaster continues. Several times during the day, I found myself shifting from sorrow to hope and then back again to uncertainty. Christmas carols put me over the edge, but then my wife and sons and I would recall something that would end up with us all howling with laughter.

I love them deeply. I love the way they respect me and yet demand my best. I love the way they are coping with their own sense of loss and uncertainty. I feel blessed.